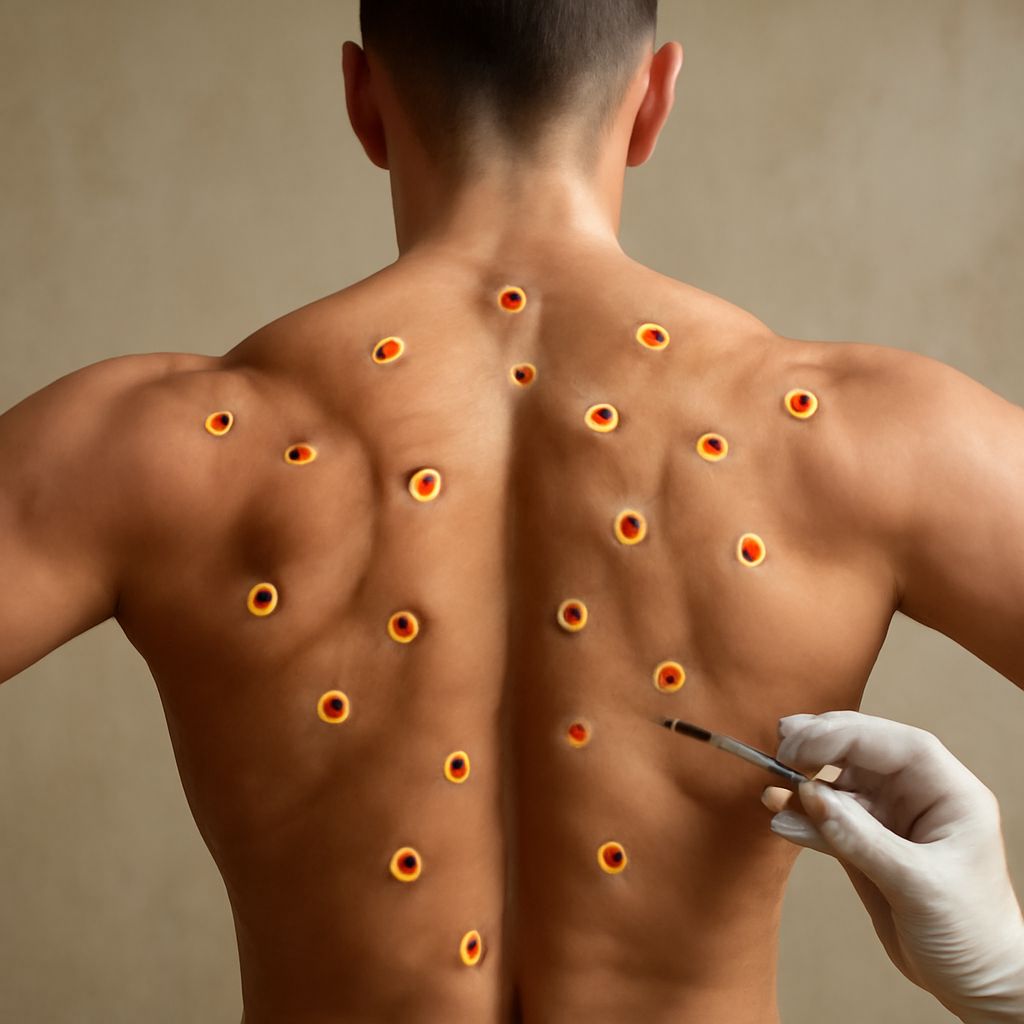
An injection into a painful muscle knot is one treatment a clinician may discuss. The result is uncertain and the needle can cause brief discomfort. Will injections into trigger points hurt? The answer varies with the person, the area treated, and the technique used.
A trigger point is a sensitive spot in a taut band of muscle that can produce local pain or pain felt elsewhere when pressed. Finding one is an examination finding, not a complete diagnosis. A clinician considers its relationship to the person’s symptoms and checks for other possible causes before recommending care. The American Academy of Family Physicians describes this assessment and the uncertainty around treatment.
What happens during the visit
A trigger point injection is performed by a trained clinician after discussing the intended target, the substance to be used, expected benefit, and risks. The clinician asks about medical conditions, allergies, medicines, and prior treatments. Blood thinners, a bleeding disorder, an infection, or broken skin at the proposed site are particularly relevant to the discussion. Prior trigger point injections and their effects are also worth mentioning.
The clinician locates the tender area by examination, cleans the skin, and inserts a needle into the selected muscle area. A small amount of liquid, often a local anesthetic, may be injected. The precise approach depends on the muscle and nearby structures. In some locations, ultrasound may help the clinician see deeper anatomy and avoid vulnerable tissues, although the CMS evidence review notes that evidence for improved outcomes remains limited.
An injection for a trigger point differs from dry needling, in which a needle is inserted without injecting medication. Both have been studied for muscle pain, but a comparison between them does not automatically show whether either treatment would help a particular person. A clinician can explain why a proposed approach fits the findings and what less invasive options remain available.
Do trigger point injections hurt during treatment?
People may feel a quick skin prick, pressure, or a brief ache as the needle reaches a sensitive muscle. The muscle can twitch, and its familiar pain may be reproduced temporarily. A trigger point injection can feel different depending on the site, sensitivity, and how many areas are treated. The person can tell the clinician if the sensation is more intense than expected so the procedure can be paused and discussed.
Do trigger point injections hurt afterward as well? Temporary soreness or bruising at the site can occur. After a trigger point is injected, the clinician should explain what to expect in that situation, how to care for the area, and whom to call if symptoms increase. The Cleveland Clinic procedure guide describes both temporary discomfort and signs that need follow-up.
The discomfort of injections into trigger points is not a reliable measure of how much benefit will follow. An uncomfortable response does not mean the procedure has succeeded, and a relatively comfortable one does not establish that it has failed. A useful measure is whether the person’s usual pain and activities change over time, using an agreed follow-up point.
What the research can and cannot tell us
Do trigger point injections work for myofascial pain? Some studies report improvement, but the size and duration of any benefit are difficult to predict for an individual. Studies of injections for myofascial trigger points differ in the muscles treated, substances used, comparison treatments, and length of follow-up. Some are small or have limitations in blinding, making it harder to separate an effect of the procedure from other influences.
The question of whether injections for trigger points work is best considered alongside those limitations. A Centers for Medicare & Medicaid Services evidence review describes inconsistent and limited-quality evidence and discusses less invasive approaches such as physical therapy and massage. The review also reports no clear superiority of one injected substance across the available studies.
A trigger point injection may be considered as one part of a broader plan rather than as a complete explanation or solution for pain. That plan might include movement or physical therapy tailored by a clinician, alongside attention to activities that aggravate symptoms. The intended result should be specific: for example, easier sleep, less discomfort at a desk, or improved ability to take part in rehabilitation. None is guaranteed.
Before proceeding, the patient can ask how a trigger point injection will be assessed, how long to wait before reviewing it, and what the next step would be if there is no meaningful improvement. Changes in daily function can be recorded along with pain intensity, since a lower pain score is only one part of the outcome.
Risks and when to seek help
Most immediate reactions are local, but injections into a trigger point also carry risks that depend on the location and substance. These include bleeding, infection, injury to a nerve or blood vessel, and a reaction to the medication. A rare puncture near the lung can cause a collapsed lung, called pneumothorax. The family physicians’ review notes that serious complications have been described in case reports; their possibility is one reason anatomy and technique matter.
After a trigger point injection, contact the clinician for fever or increasing warmth, redness, swelling, or pain at the site, which may indicate infection. Seek emergency care for new chest pain or shortness of breath, particularly after treatment near the chest or upper back, or for signs of a severe allergic reaction such as trouble breathing or swelling of the face or throat. The clinician’s discharge instructions should provide the appropriate contact information.
Questions worth asking
Before deciding about injections at trigger points, a patient can ask what finding is being treated and which other explanations for the pain have been considered. What improvement is realistic to look for, and how will it be measured? What alternatives, including physical therapy or other noninvasive care, are reasonable to discuss? Finally, which warning signs require a call, and which require emergency care? Clear answers make the procedure easier to weigh against its uncertainties.